Pain is not a neat symptom. It arrives layered with anxiety, culture, expectation, and physiology that rarely acts like a book. PUAEME008 Offer Pain Administration rests at that junction of scientific research and judgment, where the clinician has to examine promptly, deal with securely, and reassess without tunnel vision. This device is commonly utilized in prehospital and acute care contexts, across ambulance, very first responder, remote health and wellness, and occasion medicine roles. It sets well with discomfort administration training courses for registered nurses and discomfort monitoring training courses for physiotherapists who operate in urgent or area settings, and it develops a part of numerous brief courses suffering monitoring targeted at constructing sensible ability as opposed to academic breadth.
This short article concentrates on exactly how the principles within PUAEME008 play out under stress. The following scenarios and study show common problems, reasonable timelines, and the sort of trade-offs that establish whether your person obtains alleviation without undue risk.
What the device anticipates you to do well
PUAEME008 Provide Discomfort Monitoring calls for greater than familiarity with analgesic alternatives. It expects you to:
- Recognize pain quickly, evaluate it properly for the individual, and monitor for trends. Balance medicinal and non-pharmacological strategies. Apply medications from your extent of technique securely, with the right indications, dosages, and route. Anticipate negative events, especially respiratory system depression, hypotension, oversedation, and medicine interactions. Communicate plainly, including notified consent, explanation of choices, and handover to getting clinicians.
That set of assumptions underpins lots of a discomfort management certificate program. An excellent discomfort administration certification training course stresses choice making as long as pharmacology. In method, the judgment calls matter most.
The first five minutes: evaluation that acquires you time
When discomfort is severe and extreme, the lure is to reach for the fastest-acting therapy. In some cases that is right, often it creates dead spots. A structured method makes you quicker and safer:
- Get the essentials in place: air passage, breathing, blood circulation, handicap, exposure. A missed out on stress pneumothorax or hemorrhage will certainly not wait while you titrate analgesia. Use a pain scale the patient comprehends. Numerical (0 to 10) helps many adults. Encounters ranges are handy for kids or people with restricted English. In advanced mental deterioration, count on behavior hints and confirmed empirical devices if available. Clarify mechanism and warnings. Discomfort with brand-new neurological deficit, chest pain with diaphoresis, severe stomach discomfort with guarding, or discomfort after high-speed trauma changes your risk tolerance and analgesic strategy. Start non-pharmacological actions together with your analysis. Debilitate cracks, raise injured limbs, cool burns with running water for approximately 20 minutes, and provide tranquil, clear interaction. These are not soft choices, they lower nociceptive input and frequently cut medicine demands by a third or more.
The design of analysis described above functions highly hurting administration training courses that align with PUAEME008. It draws you far from auto-pilot application and toward targeted care.
Scenario 1: The thigh fracture at a country motocross track
A 27-year-old motorcyclist lays on a dust track, ideal leg reduced and on the surface rotated. Vitals on arrival: HUMAN RESOURCES 112, BP 128/76, RR 20, SpO2 98 percent on room air, GCS 15. Pain score 9 out of 10, aggravated by any movement. The occasion is 90 mins from the nearby hospital.
Judgment and sequence issue right here. Initially, incapacitate the limb and apply a grip splint if educated and indicated. The mechanical reduction in motion often goes down pain by 2 to 3 points within minutes. Next off, select an analgesic plan that fits your scope. In numerous rescue solutions, inhaled methoxyflurane or titrated IV fentanyl are first-line alternatives for extreme limb pain. If you have IV accessibility, tiny, regular doses of fentanyl can titrate swiftly with less histamine effects than morphine. If IV access is postponed or tough, methoxyflurane can bridge properly while you establish lines and get ready for transport.
Two risks reoccur in this setup. Initially, giving a huge solitary bolus of opioid in a person whose bleeding danger stays unknown. Although his vitals are secure, you need to reassess for hidden injuries, specifically if the collision included high-energy transfer. Second, ignoring antiemetics early. Vomiting in a supine, paralyzed individual causes distress and aspiration threat. Providing an antiemetic with the initial or second opioid dosage typically prevents a mess and a hazard.
Over the following hour, you will require to reassess consistently. Discomfort can increase with loading and dumping. File the fad: 9 to 6 after traction, 6 to 4 following 50 micrograms fentanyl IV titrated over 5 minutes, secure vitals, no sedation. This type of note informs the getting group what functioned, just how much, and whether you saw adverse effects. It is the sort of paperwork stressed in any kind of skilled offer pain monitoring course.
Scenario 2: A breast wall surface injury in a senior fall
An 83-year-old slips in her yard and strikes her left chest on a brick action. Currently she safeguards the area, breathing shallow, pulse 96, BP 148/84, RR 24, SpO2 94 percent, pain 8 out of 10 with deep breaths. She takes antihypertensives and a day-to-day anticoagulant for atrial fibrillation.
Chest wall surface discomfort in the senior presents a respiratory waterfall threat. Shallow breathing causes atelectasis, which invites pneumonia within days. Obtaining her to take a breath effectively matters as high as comfort. Yet elderly clients additionally lug higher dangers with opioids: slower metabolic rate, sensitivity to sedation, and interaction with existing medications.
Non-opioid scaffolding helps. If within scope, take into consideration paracetamol early at appropriate dosing and inspect previous intake to stay clear of advancing overdose. NSAIDs can reduce inflammation but needs to be avoided or utilized very carefully in patients with renal impairment, peptic ulcer disease, or high bleeding threat, which is common in this age. Entonox can assist temporary with movement, though it may be much less reliable for extended control.
If an opioid is needed, begin low and go slow. Titrate fentanyl in smaller increments, observing respiratory system rate and sedation ratings. Pair analgesia with mentoring and devices: splint the breast with a folded up towel during coughing and assist her with slow, deep breaths within her resistance. Discuss why a little pain in the short ruptureds of breathing method avoids bigger issues later on. Education and learning is an analgesic in its very own right, reducing fear-driven breath holding.

Many discomfort monitoring training courses for nurses highlight this scenario due to the fact that ward and neighborhood registered nurses typically see the delayed repercussions. A pain monitoring certification that includes senior care web content will certainly stress the balance between ample relief and breathing vigilance.
Scenario 3: Melt pain that intensifies after the cooling stops
A 9-year-old touches a warm oven door with his lower arm. Moms and dads cooled the shed under running tap water for 15 mins before you show up. The shed is shallow partial thickness with blistering over 6 percent of body area. His discomfort was a 7 throughout cooling, currently increasing to 9 as the water quits. He is troubled, declining touch.
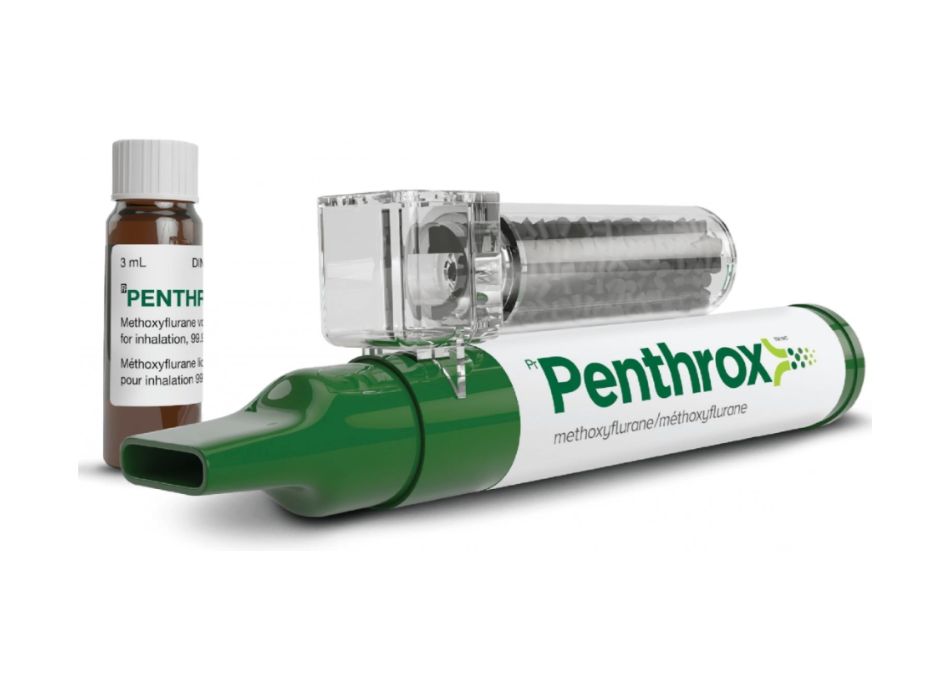
Burn discomfort spikes when cooling down ends. The skin's nociceptors remain highly active, and overview of pain management certificate anxiousness escalates the experience. Confidence alone does not cut it. If your extent includes intranasal fentanyl, it offers quick, needle-free alleviation. It is specifically valuable when IV access would certainly be a struggle in a frightened child. Dose very carefully based upon weight and reassess within minutes. If methoxyflurane is readily available and permitted for paediatric usage in your jurisdiction, it can provide good step-by-step analgesia for dressing, with familiar coaching: take a breath slowly, take breaks if dizzy.
Cover the shed with an ideal dressing that will not stick. Restricting additional direct exposure to air reduces discomfort. Keep the child warm and prevent hypothermia, a danger when air conditioning has been charitable. Youngsters degrade thermally faster than adults.
There is a typical blunder in this situation: delaying analgesia until after the first clothing is applied. In practice, you desire analgesia aboard prior to you adjust the injury. The difference between a distressing initial dressing and a bearable one will certainly form every subsequent modification. Pain monitoring training for nurses that staff emergency departments often consists of role-play around paediatric burns since the initial communication establishes the tone for household trust.
Scenario 4: The person with persistent opioid therapy and severe trauma
A 46-year-old contractor with a recorded background of persistent low neck and back pain on lasting opioid therapy drops from a ladder and presents with a distal distance fracture. He reports taking modified-release oxycodone 20 mg twice day-to-day and immediate-release 5 mg approximately three times a day. He remains in severe discomfort, 10 out of 10, sweaty and light, and mentions that "the usual stuff will not touch this."
Tolerance makes complex normal dosing. The risk is twofold. If you underdose, you extend suffering and trigger even more thoughtful stress and anxiety. If you overcorrect without regard for his standard resistance and overall direct exposure, you run the risk of oversedation as soon as the acute pain subsides. Beginning by clarifying his last dose and complete everyday morphine matching where possible. After that strategy to titrate short-acting opioid in careful increments while monitoring sedation and breathing price very closely. Think about accessories where within range: ketamine at sub-dissociative doses, laughing gas for quick step-by-step pain, or a local method if you operate in a setup where nerve blocks are within your training and protocols.
In some systems, paramedics and progressed experts can use low-dose ketamine for serious acute pain, particularly in opioid-tolerant patients. It commonly decreases the complete opioid requirement and maintains respiratory tract reflexes when dosed very carefully. Go over side effects freely, especially dysphoria. A calm, matter-of-fact explanation goes a long method to stop panic if the experience feels odd.
This holds true that separates mathematical dosing from authentic discomfort monitoring expertise. It is covered thoroughly in innovative pain administration training programs, including certification program suffering monitoring programs that deal with intricate pharmacology, resistance, and hyperalgesia.
Scenario 5: Abdominal discomfort where less is more
A 31-year-old presents with ideal lower quadrant pain for 6 hours, worsened by activity, anorexia nervosa, mild high temperature. Vitals are secure. Scientific uncertainty for appendicitis is high. He wants strong discomfort alleviation now.
Older misconceptions recommended withholding analgesia masks the medical diagnosis. Proof does not sustain that position. Proper analgesia does not conceal peritonism or change the need for imaging and surgical appointment. Still, you select agents that do not include confounders. Titrate opioid in small amounts with antiemetic cover and monitor feedback. Prevent NSAIDs if there is a risk of blood loss or kidney injury, though in steady patients without any contraindications, NSAIDs can lower opioid requirement. Do not give antispasmodics that may cloud the clinical picture, unless directed by neighborhood protocol.

In emergency pain monitoring, the skill lies in watching for change. If pain and guarding suddenly intensify, that matters more than the outright number on a scale. Your reviews lead seriousness and transport priority.
Non-pharmacological bars that genuinely change outcomes
Clinicians occasionally disregard non-drug methods as soft. In real-world technique, they often move discomfort trajectories greater than an additional 10 micrograms of opioid would.
- Positioning: Boost the hurt limb for strains and fractures. Keep the neck midline for cervical inflammation. Bend the hips slightly for peritoneal irritability. Little changes can go down pain ratings rapidly. Immobilization: A well-applied splint changes bony discomfort. Reassess blood circulation, sensation, and movement after application and at periods since swelling evolves. Temperature inflection: Continuous cool running water for thermal burns up to 20 minutes limits depth and discomfort, but prevent ice on intense musculoskeletal injuries beyond short periods, as extended topping can boost discomfort and impair tissue perfusion. Quiet, clear explanation: Unpredictability and worry enhance discomfort assumption. A minute invested outlining what you will do, and what the person will certainly really feel next, decreases catecholamines and decreases analgesic needs. Distraction and breathing: Guided breathing, simple checking, or concentrated methods audio low-tech and yet constantly help in paediatric and distressed adult patients.
Well-designed pain management training courses fold up these components into circumstances instead of noting them in isolation. They are part of the craft.
Dosing, paths, and the art of titration
Even with the exact same medicine, route matters. Intranasal shipment acquires gain access to when blood vessels are limited or time is brief. IV titration enables finer control and faster balanced out. Oral paths hardly ever suit intense extreme discomfort due to slow-moving beginning and changability in nauseated patients.
The concept that keeps medical professionals out of problem is titrate to impact with constant reassessment. Offer quick pain management courses the minimum reliable increment, wait long enough to see the impact, then determine whether to include more. Stay clear of piling doses from representatives with overlapping breathing depressant effects within brief windows, particularly benzodiazepines and opioids with each other, unless you are taking care of a particular indicator with surveillance and clear protocols.
Sedation ranges and respiratory system rate patterns are better than pulse oximetry alone. Pulse oximetry delays and can look penalty until the individual ideas right into hypoventilation. Matter respirations, expect respiratory tract obstruction noises, and be ready with basic respiratory tract maneuvers. In every pain monitoring certification program that focuses on prehospital care, teachers hammer these points since they protect against preventable harm.
Communicating dangers, consent, and expectations
Patients desire alleviation. They also wish to really feel safe and educated. A brief, clear discussion builds both. State what you recommend, why, the main dangers in simple terms, and just how you will expect them. With kids, involve caregivers proactively and framework choices in age-appropriate language. When English is limited, utilize interpreters where feasible or verified communication devices for discomfort scales. Record consent as part of your regimen, not as an unique case.
Handovers are another point where pain management either continues efficiently or hinders. Include the standard discomfort score, what you attempted and in what doses, the patient's reaction, negative effects, and any type of non-pharmacological actions in position. If you started a titration strategy, state so. Smooth handover is as crucial as the first dose.
When the playbook changes: cultural and trauma-informed care
Pain is infiltrated society and past experiences. Some neighborhoods reduce spoken expression of suffering. Others make use of details phrases to connect intensity without numerical ranges. Try to match the patient's design instead of forcing a stiff format. For clients with an injury background, sudden touch or crowded areas can set off dissociation or panic. Introduce your activities prior to you do them, request for consent where possible, and offer the person some control, also if small, such as selecting which arm to utilize for monitoring.
These are not just precisions. They impact analgesic needs, collaboration with treatments, and general end results. Programs that offer discomfort management training for registered nurses increasingly consist of trauma-informed structures because they change day-to-day practice.
The restraint trap: anxiety and pain
Agitated people frequent pain. If you grab physical restraint first, discomfort usually worsens, frustration rises, and the risk of injury rises. Begin by assuming pain becomes part of the image. Treat most likely resources while involving verbally. If chemical sedation is needed for safety, titrate with representatives that also offer analgesia when suitable, and continue to search for the underlying excruciating stimulus. It is surprisingly common to find a missed fracture or misplacement when the person settles.
Data you will actually make use of: what to tape-record and why
Pain charts need to narrate, not simply a number. The very best paperwork sets a score with context. "Discomfort 8 at remainder, 10 with movement, after splinting and 100 micrograms fentanyl collective IV currently 3 at remainder, 6 with activity, RR 16, sharp, no nausea or vomiting." That line allows a getting medical professional proceed titration smartly. For audits and for your very own learning, it likewise provides a map of what worked.
In a pain management accreditation program, especially those developed as a pain administration certificate for prehospital or occasion medical professionals, you will certainly typically be asked to send case reflections. One of the most useful reflections evaluate timing, series, and monitoring, not just drug choice.
Where PUAEME008 fits within wider training
PUAEME008 Provide Pain Administration often shows up together with trauma and medical emergency situation systems, developing component of a bundle suffering monitoring training. For clinicians constructing a profession portfolio, a discomfort monitoring certification enhances wider qualifications and supports credentialing conversations with employers. If you already hold a basic pain administration accreditation, this device adds the functional layer: quick analysis, short half-life representatives, step-by-step analgesia, and the self-control of watching for problems in unchecked environments.
Providers offer various formats. Some market short programs hurting administration targeted to registered nurses in severe wards and access setups. Others tailor discomfort administration programs for physiotherapists, concentrating on subacute musculoskeletal pain, taping, movement strategies, and non-opioid pharmacology understanding. When assessing a supply discomfort monitoring training course, look for simulation time, scenario selection, regional medication protocols, and teacher experience. A course packed with talks and slim on hands-on method leaves spaces where it counts.
Case study representations: three patterns that keep revealing up
- Timing beats strength. Early, modest analgesia plus great splinting usually achieves far better results than waiting and then supplying large doses under stress. The review is where you discover difficulty. After the very first dosage or treatment, reassess with fresh eyes. Essential indicators, discomfort high quality, and action to motion can expose missed out on injuries or evolving physiology. Teach while you treat. Describe what you are doing and why. Patients that comprehend the plan work together far better and report discomfort a lot more properly. That responses loop boosts your dosing and safety.
These patterns seem straightforward, yet in busy scenes they are easy to neglect. Discomfort management training installs them via repeating under varied conditions.
Common pitfalls and what to do instead
Many unfavorable occasions and suboptimal outcomes map back to a list of mistakes. 3 stand apart. Initially, ignoring the influence of non-pharmacological measures. Second, stacking sedatives. Third, anchoring on a solitary diagnosis when discomfort habits does not match the tale. The different method is easy to state and tougher to practice: focus on mechanical measures early, avoid combined respiratory downers unless plainly shown and kept track of, and keep examining your working medical diagnosis against brand-new information.
Building self-confidence: method that counts
No program changes repetition. If your solution runs simulation days, volunteer for the discomfort stations. Practice intranasal shipment in a sensible timeline, IV titration while taking care of scene babble, and connecting with distressed households. Ask instructors to add curveballs: a patient who overreports discomfort, one that underreports, an unexpected drop in high blood pressure after an opioid dosage. The point of a pain administration accreditation training course is not just to pass evaluation, it is to develop an internal collection of patterns so you can respond steadly when details shift.
Peer conversation accelerates learning. After challenging calls, debrief specifically on pain choices. What would you transform following time? Would certainly previously splinting have decreased application? Did we miss out on an antiemetic possibility? Did handover show the strategy? In time, these conversations lift the entire group's standard.
Final idea: alleviation with respect
Providing discomfort relief is both humane and professional. The regard component suggests you eliminate experiencing without creating fresh threats, you pay attention to the client's language for discomfort, and you do not require them right into your pace without clarifying why. PUAEME008 Supply Discomfort Monitoring offers the scaffolding. Experience completes the voids and polishes the judgment. Whether you are pursuing a pain management certification, tasting short training courses hurting monitoring to hone your side, or embedding PUAEME008 provide pain monitoring within a more comprehensive capability framework, the objective is the same: accurate assessment, reliable alleviation, and vigilant follow-up. If you can provide those 3 under pressure, the rest comes under place.